

Facial Vascular Anatomy for Aesthetic Injectors: Key Structures and Safety Considerations
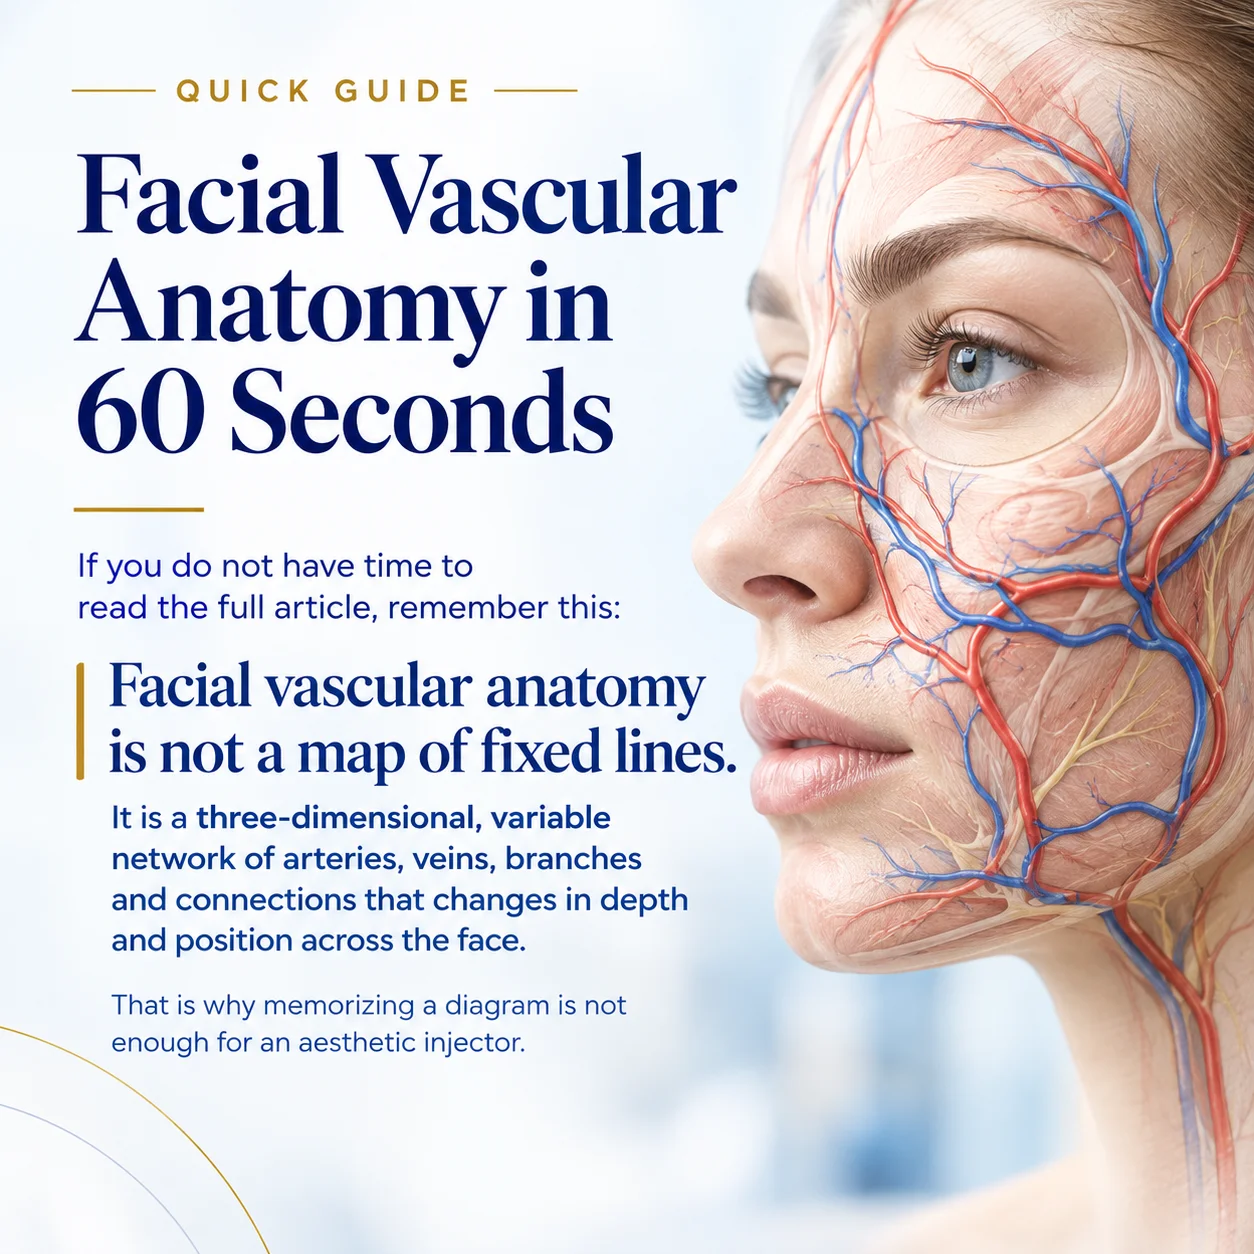
Figure 1: Facial arterial networks and their anatomical relationships

Figure 2: Anatomical variation in regional vascular patterns
The CBAM 5D Vascular Anatomy Model
When assessing any facial region, ask:
REGION — Where am I?
↓
LAYER — What anatomical plane am I considering?
↓
VESSEL — Which vessels may be present?
↓
VARIATION — How might this anatomy differ in this patient?
↓
CONNECTION — Where can this vascular territory communicate?
Bottom line: The goal of vascular anatomy education is not to memorize every artery. It is to build a three-dimensional mental model that improves anatomical reasoning before and during aesthetic treatment planning.
For the broader anatomical foundation—including facial layers, muscles, fat compartments, retaining structures, nerves, vessels and aging—see the CBAM Facial Anatomy Training Guide.
Why Facial Vascular Anatomy Matters in Aesthetic Medicine
Facial injectable treatments are performed within one of the most anatomically complex regions of the body.
Beneath the visible surface lie multiple tissue layers containing:
- arteries;
- veins;
- nerves;
- muscles;
- fat compartments;
- retaining structures;
- periosteum;
- bone.
For aesthetic injectors, understanding this anatomy is not simply an academic exercise.
It contributes to patient assessment, treatment planning, anatomical orientation and complication awareness.
This becomes particularly important with dermal fillers because inadvertent vascular compromise can result in serious complications, including tissue ischemia and necrosis. Published literature also documents rare but severe ocular and neurological consequences associated with filler-related vascular events.
The appropriate conclusion, however, is not:
"Learn the arteries and filler becomes safe."
A more accurate conclusion is: Better anatomical understanding can support risk reduction, but anatomy does not eliminate procedural risk.
That distinction should remain at the center of aesthetic anatomy education.
Stop Thinking of Facial Arteries as Lines on a Diagram
One of the biggest limitations of learning anatomy exclusively from illustrations is that diagrams flatten a three-dimensional face into two dimensions.
A textbook may show an artery traveling from Point A to Point B.
But an injector needs more information.
For example:
- What tissue layer is it in?
- Does its depth change?
- What structures surround it?
- What branches may arise?
- Where might it communicate with another vascular territory?
- How much anatomical variation is possible?
- Has surgery, trauma or another procedure potentially altered the anatomy?
This is why vascular anatomy for aesthetic medicine should be understood spatially.
The face is not a map.
It is a layered anatomical environment.
Understanding the CBAM 5D Model in Detail
1. Region
Start with the anatomical region.
For example:
- forehead;
- glabella;
- temple;
- nose;
- cheek;
- nasolabial region;
- lips;
- chin.
Different regions have different vascular relationships.
But region alone is insufficient.
2. Layer
Next ask: What anatomical layer are we discussing?
The relationship between skin, subcutaneous tissue, superficial musculoaponeurotic structures, muscles, deeper fat compartments and periosteum changes across the face.
A vessel's relevance therefore cannot be understood purely from its surface projection.
This is one reason why layer-by-layer anatomical education is so important for injectors.
3. Vessel
Which major arteries, branches or veins are relevant to this region?
This step moves beyond simply memorizing the facial artery.
Depending on the region, relevant structures may arise from different vascular systems.
4. Variation
Human anatomy is variable.
The location, branching pattern, dominance and depth of vessels can differ between individuals.
That means:
- A textbook map describes common anatomy—not guaranteed anatomy.
- This is one of the most important principles an injector can learn.
5. Connection
Finally: Where does this vascular territory connect?
Anastomoses and communications between vascular systems are clinically important because the consequence of vascular compromise is not necessarily limited to the point where a procedure occurs.
Understanding these connections transforms vascular anatomy from memorization into clinical reasoning.
The Facial Artery: A Major Landmark, Not a Fixed Road
The facial artery is one of the most important arteries to understand in aesthetic medicine.
It originates from the external carotid arterial system and enters the face around the lower border of the mandible before following a generally tortuous course.
As it travels superiorly, branches contribute to vascular supply in several important facial regions.
These include structures associated with:
- the lower face;
- lips;
- nasolabial region;
- nose;
- medial face.
But the facial artery should not be imagined as a perfectly predictable line.
Its course and branching pattern can vary.
This is exactly why surface landmarks should be combined with deeper anatomical understanding.
Lip and Perioral Vascular Anatomy
The lips are among the most frequently treated areas in aesthetic medicine.
They are also highly vascular.
The superior and inferior labial arteries are important components of the perioral vascular system.
Their relationships with the orbicularis oris muscle and surrounding tissues are clinically relevant, but variation exists in their course and depth.
For the injector, the key lesson is not to memorize one universal diagram of a labial artery.
It is to understand that lip treatment takes place within a dynamic vascular and muscular structure.
The lips also demonstrate an important broader principle:
Small treatment area does not mean simple anatomy.
The Nasolabial and Medial Facial Region
As the facial artery continues through the midface, its relationship to the nasolabial region becomes particularly relevant.
The artery's position and depth can vary as it travels superiorly.
This makes simplistic rules such as:
"The vessel is always here."
potentially misleading.
A more clinically useful question is:
What vascular structures could be encountered in this region, in which layers, and with what degree of anatomical variation?
That reasoning is transferable to almost every injectable region of the face.
Why the Nose Deserves Particular Vascular Attention
The nose is anatomically important because its vascular supply involves interconnected branches from both external and internal carotid systems.
These relationships contribute to why vascular events in this region can have consequences beyond local skin injury.
The relevant lesson for practitioners is not simply that the nose is a "danger zone."
That label is too simplistic.
The real issue is the combination of:
- vascular density;
- communicating vessels;
- variable anatomy;
- limited tissue environment;
- connections involving the ophthalmic circulation.
Understanding why a region presents vascular concern is more valuable than memorizing a red area on a diagram.
Glabella and Forehead: Think Beyond the Surface
The glabella and forehead involve vessels associated with the ophthalmic arterial system, including supraorbital and supratrochlear territories.
This is particularly important because the ophthalmic circulation ultimately relates to ocular structures.
Published reviews of filler-associated vascular events have repeatedly emphasized the importance of upper facial anatomy when considering severe complications.
The clinical lesson again is not that one anatomical coordinate is dangerous while another is safe.
It is that practitioners need to understand the vascular network and its potential connections.
The Temple: A Layered Anatomical Problem
The temporal region is an excellent example of why two-dimensional anatomy is insufficient.
The temple contains multiple anatomical layers and clinically relevant vascular structures, including branches of the superficial temporal vascular system.
Recent anatomical research continues to examine vascular relationships and variation in the temporal region because its layered anatomy is complex.
For practitioners, the temple demonstrates the importance of asking:
Which layer am I in?
before asking: Where is the vessel?
Those are different questions.
And both matter.
The Midface Is Not One Anatomical Unit
The cheek is often casually discussed as though it were a single treatment area.
Anatomically, it is much more complicated.
The midface contains:
- multiple fat compartments;
- retaining structures;
- muscles;
- infraorbital structures;
- branches of the facial vascular system;
- transverse and regional vessels;
- deep and superficial tissue relationships.
As a result, "cheek anatomy" is too broad a concept for precise clinical reasoning.
A practitioner should instead think regionally and layer by layer.
Why Anatomical Variation Changes Everything
Imagine learning that an artery "usually" travels through a particular location.
The word usually matters.
Human vascular anatomy contains meaningful variation.
Two patients may share the same external facial landmarks while having different vascular relationships beneath the skin.
Variation can involve:
- branching;
- course;
- depth;
- vessel dominance;
- anastomotic relationships.
Prior surgery, trauma, scarring or other interventions may add further complexity.
This is one reason modern anatomical education increasingly emphasizes probability and variation rather than rigid coordinates.
Are There Really "Safe Zones" for Facial Injectables?
The term safe zone is appealing.
It suggests certainty.
But facial anatomy rarely provides absolute certainty.
A region may be considered relatively lower risk under specific circumstances.
That does not mean it is anatomically guaranteed to be free of important vessels.
A more accurate vocabulary is:
- higher-risk region;
- lower-risk region;
- expected vascular course;
- common anatomical relationship;
- anatomical variation;
- risk-reduction strategy.
This language better reflects clinical reality.
Anatomical knowledge reduces uncertainty. It does not eliminate uncertainty.
That is a more useful mindset for aesthetic practitioners.
Why Vascular Connections Matter
One of the most important concepts in facial vascular anatomy is anastomosis.
Blood vessels do not always function as isolated pipelines.
Branches from different vascular territories can communicate.
In the face, communications between branches of the external carotid system and branches associated with the ophthalmic circulation are particularly important in understanding why certain vascular complications may extend beyond the immediate injection site.
This is also why memorizing the location of individual arteries is not enough.
The practitioner needs to understand the network.
What Does Vascular Occlusion Mean in Aesthetic Medicine?
Vascular occlusion occurs when blood flow through a vessel becomes compromised.
In the context of dermal filler procedures, this can occur through mechanisms including intravascular introduction of material or vascular compression.
The resulting reduction in tissue perfusion can lead to ischemic injury.
Although serious filler-associated vascular complications are uncommon, the potential consequences can be substantial.
A 2026 review of hyaluronic acid filler-associated vascular occlusion emphasized that inadvertent arterial injection can result in tissue damage, scarring, visual loss and, in severe circumstances, neurological complications.
This is why prevention, early recognition and appropriate escalation are essential parts of injectable education.
Anatomy Helps Reduce Risk. It Does Not Eliminate It.
This distinction deserves its own section.
A practitioner can know facial anatomy extremely well and still encounter anatomical variation.
Anatomy is one layer of safety.
Others include:
- appropriate patient assessment;
- product knowledge;
- understanding treatment indications;
- practical procedural training;
- complication recognition;
- emergency preparedness;
- professional judgment;
- working within legal scope of practice.
No anatomy course should imply that anatomical knowledge makes injectable treatment risk-free.
Instead, anatomy should improve the quality of clinical decisions made within an inherently variable biological system.
Anatomy Is Becoming More Dynamic
Traditional anatomical education relies heavily on:
- textbooks;
- illustrations;
- cadaver dissection;
- anatomical landmarks.
These remain valuable.
But contemporary aesthetic medicine is increasingly exploring real-time imaging as another layer of anatomical information.
Recent literature has examined high-resolution and Doppler ultrasound for identifying facial vessels, anatomical variants and vascular changes in higher-risk injectable regions.
This does not make ultrasound a substitute for foundational anatomy.
Rather, it illustrates an important evolution:
Aesthetic anatomy is moving from memorizing average anatomy toward understanding patient-specific anatomy.
For practitioners, that is an important conceptual shift.
Why Cadaver-Based Anatomy Adds Something a Diagram Cannot
A diagram is clean.
Real anatomy is not.
Cadaver-based education can help practitioners visualize actual relationships between:
- skin;
- fat;
- fascia;
- muscle;
- vessels;
- nerves;
- periosteum;
- bone.
It also helps learners appreciate that anatomical structures exist within layers rather than as isolated colored lines.
This is particularly valuable for understanding how vascular structures relate spatially to other tissues.
The CBAM Facial Anatomy Cadaver Certificate Course combines facial anatomy, facial aging and cadaver workshop education, including layer-by-layer anatomical study and vascular relationships.
For practitioners who learn best by seeing actual tissue relationships, cadaveric education can bridge the gap between textbook anatomy and three-dimensional anatomical reasoning.
What a Vascular Anatomy Diagram Cannot Teach You
A diagram can show you where an artery commonly travels.
It cannot fully teach you:
- how tissue layers feel;
- how structures relate in three dimensions;
- how anatomy varies from one individual to another;
- how facial aging changes anatomical relationships;
- how prior procedures may alter anatomy;
- how clinical judgment develops;
- how to respond when anatomy does not match expectation.
That is why anatomy education should progress from:
Memorization
↓
Spatial Understanding
↓
Variation Awareness
↓
Clinical Interpretation
↓
Risk-Aware Decision-Making
The objective is not to create practitioners who can label every artery on an exam.
The objective is to develop practitioners who can think anatomically.
Facial Anatomy Should Be Learned Region by Region
One useful approach for aesthetic practitioners is to study each treatment region using the same questions.
For example:
Forehead
- What are the major layers?
- Which muscles are present?
- Which vascular structures are relevant?
- Which nerves are relevant?
- How can anatomy vary?
- Which structures communicate with adjacent regions?
Temple
Ask the same questions.
Nose
Again, the same questions.
Lips
Again.
Midface
Again.
Over time, this builds a reusable anatomical reasoning system rather than a collection of disconnected facts.
The CBAM 5D Regional Checklist
Before thinking about any facial treatment region, return to five questions:
- REGION — Where am I anatomically?
- LAYER — Which tissue plane am I considering?
- VESSEL — Which important vascular structures may be present?
- VARIATION — What might differ from the textbook?
- CONNECTION — Where can this vascular territory communicate?
This framework can be applied repeatedly across facial regions.
It is intentionally simple.
The anatomy itself is not.
Where Facial Anatomy Fits Into Injectable Education
Aesthetic injectable education should not begin with memorizing product names or isolated techniques.
A stronger progression is:
Facial Anatomy
Understand the anatomical environment.
↓
Facial Assessment
Understand the individual patient's structure, proportions and treatment goals.
↓
Product and Treatment Principles
Understand what a treatment is intended to achieve.
↓
Treatment Planning
Connect anatomy, assessment and treatment selection.
↓
Complication Awareness
Understand what can go wrong and why.
↓
Supervised Practical Skill Development
Translate theoretical knowledge into technique under appropriate training conditions.
This progression matters because injectable procedures are highly technique-sensitive.
Online education can build a substantial anatomical and clinical foundation, but it does not replace supervised hands-on skill development where such practical training is required.
Focused Anatomy Training or Complete Injectables Education?
The right educational pathway depends on what the practitioner is trying to learn.
If Your Primary Goal Is Anatomy
Practitioners who want deeper understanding of facial layers, vascular structures, aging and cadaveric relationships can explore the CBAM Facial Anatomy Cadaver Certificate Course.
This is the focused pathway.
If Your Goal Is Broader Injectable Education
Practitioners seeking education that connects anatomy with Botox, dermal fillers, PRP/PRF, skin boosters, patient assessment and complication awareness can explore the CBAM Online Injectables Package.
The current package brings several injectable-related areas into one structured learning pathway.
This creates two distinct routes:
- Deep anatomical focus → Facial Anatomy & Cadaver
- Broader injectable pathway → Online Injectables Package
The choice depends on the learner's existing background and educational goals.
What Studies Cannot Fully Teach an Injector
Scientific literature is essential.
But there is an important limitation.
A systematic review can describe common vascular patterns.
A cadaveric study can demonstrate anatomical relationships.
Imaging studies can reveal variation.
A complication review can identify patterns associated with adverse outcomes.
None of these alone creates clinical competence.
Competence emerges from combining:
- Evidence
- Anatomical knowledge
- Clinical reasoning
- Appropriate practical training
- Complication preparedness
This distinction is especially important in aesthetic medicine, where knowing what usually happens must be balanced against recognizing what could be different in the patient in front of you.
The Most Important Lesson in Facial Vascular Anatomy
The most valuable thing an aesthetic injector can learn is not the exact location of one artery.
It is a way of thinking.
Do not ask only:
"Where is the vessel?"
Ask:
Where am I?
Which layer am I considering?
Which vessel could be here?
How could this anatomy vary?
Where does this vascular territory connect?
That is the difference between memorizing anatomy and reasoning anatomically.
Clinical Takeaways
Facial vascular anatomy is central to aesthetic injectable education because the face contains a complex, interconnected and variable vascular network.
Practitioners should understand that:
- vascular anatomy is three-dimensional;
- vessel depth can change across a region;
- anatomical variation is clinically important;
- vascular territories communicate;
- some facial regions warrant heightened awareness;
- anatomical knowledge supports risk reduction but cannot eliminate risk;
- textbook diagrams should be treated as models, not guarantees;
- anatomy should be integrated with patient assessment, treatment planning, complication recognition and appropriate practical training.
The most useful mental model is therefore not a collection of red lines on a face.
It is:
REGION → LAYER → VESSEL → VARIATION → CONNECTION
Once that framework becomes habitual, facial vascular anatomy becomes more than something to memorize.
It becomes part of clinical reasoning.
Frequently Asked Questions
Why is facial vascular anatomy important for aesthetic injectors?
Which facial areas require particular vascular awareness?
Is there a completely safe zone for dermal filler injections?
What is vascular occlusion after dermal filler treatment?
Can facial anatomy vary between patients?
Is knowing facial anatomy enough to perform injectable treatments safely?
Does cadaver training help with facial anatomy?
Can facial anatomy be learned online?
Ready to Deepen Your Vascular Anatomy Knowledge?
Master facial vascular anatomy through cadaver-based education and clinical reasoning frameworks designed for aesthetic practitioners.
Explore the Cadaver Certificate Course
Have questions or want to discuss your learning goals?
Share your thoughts in the comments below